20240517_121831

How Exercise May Shape ‘Good Cholesterol’ in People Recovering From Gastrointestinal Cancers

Author:  Pousali Chatterjee (AllCaN PhD Candidate)

Background

The recovery after gastrointestinal cancer surgery extends far beyond the completion of treatment. Many patients experience a prolonged period of psychological, physiological and metabolic disruption, accompanied by a gradual rebuilding of strength and confidence. Lifestyle‑based approaches, particularly structured exercise programmes, are increasingly recognised as important components of this recovery process, not only because they improve physical capacity but because they appear to influence several biological pathways that remain altered long after surgery.

One of the areas my PhD focuses on is how these lifestyles changes intersect with inflammation, a process that plays a central role in metabolic health, immune function, and, potentially, cancer risk. To study this, I examine a particle that circulates in your blood called high-density lipoprotein (HDL) or more commonly referred to as your ‘good cholesterol’. While much is known about HDL particles in the setting of heart disease, little is known about their role in cancer biology and this is a major focus of my thesis.

HDL: More Than a Heart-Health Number

HDL particles are made up of many different types of fats and proteins with over 280 proteins carried on these particles around the blood stream. These proteins dictate the function of the particles. In healthy individuals HDL particles carry a large cargo of proteins that can reduce inflammation and exert antioxidant effects – in this setting HDL is anti-inflammatory. In the setting of heart disease, there is a switch in the types of proteins on HDL with increased accumulation of pro-inflammatory proteins and loss of anti-inflammatory proteins which results in a loss of the protective anti-inflammatory properties of the particles. Importantly, these changes in the protein composition of HDL particles are not captured in currently used clinical tests in the clinic (such as your HDL-cholesterol levels); the changes in protein composition often occur even in the presence of normal levels of HDL-C.

Because the proteins on HDL change in response to disease, they can provide valuable information about a person’s heart and metabolic health. My PhD research aims to investigate whether similar changes occur in gastrointestinal cancers. More than 30% of HDL particles originate in the digestive system, meaning they may carry proteins that reflect what is happening in the gut. By measuring these proteins from a simple blood sample, we hope to develop new ways to better understand and potentially detect gastrointestinal cancers.

The first aim of my PhD project is to comprehensively profile HDL-associated proteins in individuals with gastrointestinal cancers, as well as those at high risk of developing these cancers. By identifying novel HDL protein signatures associated with cancer risk, we aim to discover biomarkers that could help identify individuals before disease progression to a metastatic stage, enabling earlier intervention and improved clinical outcomes.

Where Exercise Fits In

Exercise exerts a broad range of positive effects on metabolic and inflammatory pathways. Beyond improving cardiorespiratory fitness, regular physical activity can reduce low‑grade inflammation, modulate immune cell function, and influence lipid handling. These processes intersect directly with HDL biology. If exercise can shift HDL away from an inflammatory profile and toward a more protective one, it may help explain why lifestyle interventions improve long‑term outcomes in cancer survivors.

The second aim of my thesis therefore is to investigate how exercise interventions in patients recovering from gastrointestinal cancers influence the protein composition of HDL particles. This work will provide greater insight into the molecular mechanisms through which exercise may support recovery, reduce recurrence risk, and promote long-term remission and overall health.

Connecting Research to Real Patients: The ReStoRe Trial

A central component of my project involves analysing serum samples from participants enrolled in the ReStoRe trial, a structured lifestyle and diet intervention programme designed for individuals recovering from gastrointestinal cancer surgery. The programme provides supervised exercise, nutritional guidance, and behavioural support, creating a controlled environment in which we can examine how lifestyle changes translate into measurable biological effects.

By studying HDL‑associated proteins in these samples, we aim to determine whether exercise induces detectable shifts in HDL composition. Specifically, we are interested in whether the particle loses inflammatory proteins, regains protective ones, or shows evidence of altered GI‑derived signalling. These molecular changes may help identify individuals who respond particularly well to exercise‑based interventions and, conversely, those who may require additional support.

Why This Matters: Clinical Relevance

If exercise can modulate HDL composition in a favourable direction, it provides a practical explanation for why lifestyle-based recovery programmes improve patient outcomes. Beyond the molecular insight, this creates a clinically useful tool: HDL could act as a non-invasive indicator of recovery quality, helping clinicians distinguish between patients who are progressing well and those who may require more targeted follow-up. Such stratification has direct implications for service efficiency, reducing unnecessary appointments, preventing over-monitoring of low-risk individuals, and allowing clinical teams to focus resources on patients with persistent inflammatory or metabolic disruption.

Looking Ahead:  Scientific Vision

By examining how exercise reshapes HDL in  patients in recovery from GI-related cancer,  we aim to capture the molecular consequences of lifestyle intervention in real time. This approach moves beyond traditional clinical metrics and instead uses HDL as a window into the internal environment during recovery, offering insight into how modifiable behaviours influence long-term health trajectories in individuals at risk of oesophageal cancer and other GI conditions.

HDL Modulation: Mechanistic Pathway

HDL carries proteins involved in inflammation, complement activation, oxidative stress, and lipid transport. When the particle becomes enriched with inflammatory proteins: a pattern common in obesity and metabolic strain, it may signal a biological state associated with slower recovery and higher clinical demand.

If exercise can reverse some of these changes, reducing the inflammatory burden on HDL or restoring proteins with protective roles, HDL becomes a useful molecular readout of recovery trajectory. This information can help clinicians tailor follow‑up intensity, provide streamline interventions, and allocate resources more effectively.

In this way, HDL modulation offers a biologically grounded mechanism for refining cancer care pathways.

IMG_5203

What is Immunotherapy in Oesophageal Cancer?

What is immunotherapy?

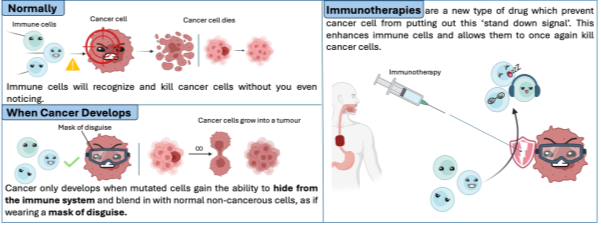
Immunotherapy refers to an umbrella of drugs which enhance a patient’s own immune system to kill cancer cells. Immunotherapies are a relatively new type of treatment which have revolutionised the prognosis of many cancer types. Turning previously dismal prognosis cancers into ones with relatively favourable outcomes, but how do these work?

Normally, the immune system is able to kill cancer cells before they become an issue.  In a nutshell, cancer only becomes problematic when it is able to hide from the immune system and grow into tumours, essentially putting on a mask of disguise. We are specifically looking at a type of immunotherapy called immune checkpoint inhibitors, which in essence, prevents cancer cells from hiding from the immune system.

Improving immunotherapy in Oesophageal cancer

Unfortunately like many other cancers which are solid tumours, oesophageal cancer patients tend to not respond to immunotherapy. Only around 1 in 5 oesophageal cancer patients will benefit from this treatment option. While there are many reasons as to why this is the case, our research aims to improve this number by combining immunotherapy with other new treatment options which further improve the immune system’s ability to recognise cancer cells. We hope that this treatment approach could one day be used to offer more effective treatment to a wider range of oesophageal cancer patients.

Diana Cooke AllCan

Barrett’s Oesophagus Beyond the Clinic

Being diagnosed with Barrett’s Oesophagus can feel overwhelming, particularly when many people have never heard of the condition before. For many people, the diagnosis is quickly followed by searching online to better understand what Barrett’s Oesophagus actually is, what it means for their health, and what they should do next. While Barrett’s Oesophagus is linked with an increased risk of oesophageal cancer, it is important to remember that Barrett’s Oesophagus is not cancer, and most people with the condition will never develop oesophageal cancer.

Alongside medication and surveillance, lifestyle modification is often discussed as an important part of managing Barrett’s Oesophagus and reflux symptoms. Conversations around diet, physical activity, weight management, smoking, and alcohol can suddenly become a much bigger part of everyday life. Many people are left trying to understand what these changes actually mean in practice, how realistic they feel to maintain, and how they fit around everyday life.

As part of my research, I recently conducted a scoping review, a type of study that brings together and examines findings from existing research, looking at lifestyle behaviours in people living with Barrett’s Oesophagus. The review included 55 studies representing 51 unique patient cohorts from several countries across Europe, North America, Asia, and Australia. One of the clearest findings was that many people struggle with the very things they are often advised to change.

Across the studies, around one-third to one-half of people are overweight, while up to half were living with obesity. Low levels of physical activity were also common, with many studies showing that more than half of participants were not active enough to meet recommended exercise guidelines. Diet was another area many people struggled with, with sometimes only 10% of people following dietary advice aimed at reducing symptoms of reflux. Smoking and alcohol rates also varied quite a lot, with some studies reporting relatively low numbers of smokers and drinkers, while others found much higher numbers.

Despite lifestyle advice often being part of Barrett’s Oesophagus management, there was surprisingly little research exploring people’s experience of making these changes in everyday life.

These findings matter because they tell us that people struggle with eating a healthy diet or being physically active, despite the advice that they receive when diagnosed with Barrett’s Oesophagus. It suggests that many people may need more support, guidance, and practical advice than they are currently receiving.

The challenge is that lifestyle change is rarely as straightforward as it sounds. For many people, hearing the words “lifestyle change” after diagnosis can feel overwhelming, especially when it sounds like you are expected to completely overhaul your life overnight.

In reality, many people describe change as being much more gradual than that, often involving small adjustments over time rather than dramatic changes all at once. People living with Barrett’s Oesophagus who are now taking part in our interview study tell us that certain foods, large meals, or eating late at night seem to worsen reflux symptoms. Others focus on becoming more physically active, losing weight gradually, remembering to take medication more consistently, or avoiding lying down immediately after eating.

For many people, increasing physical activity does not mean suddenly joining a gym or feeling like they need to start intense exercise straight away. It can be as simple as going for more regular walks, getting off the bus a stop earlier to incorporate a short walk, taking the stairs more often, or finding small ways to move more during the day. Diet can feel similar. Healthy eating does not have to mean cutting out every food you enjoy. For some people, it may involve smaller meal portions, eating earlier in the evening, cooking at home more often, or paying attention to foods that seem to worsen reflux symptoms.

Making small lifestyle changes can also help people feel a greater sense of control after diagnosis. When so much about Barrett’s Oesophagus can feel uncertain, focusing on manageable day-to-day habits may help people feel more actively involved in their own care.

It is easy to tell someone to “eat healthier” or “exercise more”, but real life is much more complicated than that. Work, family responsibilities, stress, finances, symptoms, tiredness, and simply trying to keep up with everyday life can all make change difficult. Many people know what they “should” do, but feel unsure where to start or struggle to maintain changes long term.

Barrett’s Oesophagus can feel difficult to explain to other people because it is often an invisible condition and can come with a lot of uncertainty. Many people feel physically well most of the time, while still living with regular medication, surveillance endoscopies, reflux symptoms, and the uncertainty that can come with long-term monitoring. It can sometimes feel like carrying around a condition that is invisible to everyone else, but still takes up space in your mind.

If you have recently been diagnosed, a few small practical things may help:

  • Keep a note of any questions that come to mind between appointments. It is easy to forget them once you are sitting in front of a doctor or nurse. Ask doctors to explain unfamiliar medical terms again if needed.
  • Avoid overwhelming yourself with endless online searching. Barrett’s Oesophagus and reflux can affect people differently, and lifestyle advice is often not one-size-fits-all.
  • If you are asked to make lifestyle changes, focus on one or two manageable changes first rather than trying to change everything at once.
  • Try to find forms of movement that realistically fit into your normal routine. For many people, consistency feels more manageable than aiming for intense exercise straight away.
  • If you are trying to make dietary changes, paying attention to when reflux symptoms worsen can sometimes help you identify patterns. Some people find that large meals, eating late at night, or certain foods seem to trigger symptoms more than others.

Most importantly, remember that you are not expected to figure everything out immediately.

Living with Barrett’s Oesophagus is not just about managing a condition. It is also about managing uncertainty, balancing advice with everyday life, and finding what works for you. And if you are finding that difficult, you are far from alone.

thumbnail_image (2) (1) (1)

Coping with Barrett’s Oesophagus: Emotional and Mental Well-Being

When people talk about living with Barrett’s oesophagus the focus is on treatment, endoscopies and long-term monitoring. But for many people, the psychological and emotional impact of living with a precancerous condition can be as challenging as the physical symptoms.

A diagnosis often involves feelings of fear, anxiety and uncertainty, especially around cancer risk and ongoing surveillance. These worries, especially when combined with persistent reflux symptoms, can negatively affect health-related quality of life (HRQoL).

Stress, Anxiety and the Gut.

Stress plays a major role in gastrointestinal health, triggering a noticeable symptom increase even when reflux is under control. Acute and prolonged stress can disrupt digestion, increase acid production and heighten oesophageal sensitivity, worsening an underlying gastrointestinal reflux disease (GORD). Over time these symptoms worsen GORD, which may contribute to the development or progression of Barrett’s oesophagus. Patients recognize the cycle too well – stress worsens symptoms and those symptoms in turn increase stress.

Patient Experiences

People living with Barrett’s oesophagus can experience difficult thoughts and feelings in their everyday lives, such as:

  • Persistent anxiety about progressing to cancer (cancerphobia)
  • Uncertainty about what the future holds
  • “Scanxiety”- before surveillance appointments
  • Concerns about treatment decisions
  • Feeling unable to articulate their fears and feelings to loved ones
  • A sense that loved ones and peers don’t understand
  • Feelings of isolation, social and emotional withdrawal

Emotional pressures can intensify physical symptoms, triggering a cycle of distress and symptom exacerbations that disrupt household routines, finances and relationships.

Quality of Life

Living with persistent feelings of uncertainty, reflux, and fear can reduce HRQoL. How well someone copes often depends on factors such as –

  • How they understand their condition
  • Reflux Management.
  • Trust in their care management.
  • How effective their social and emotional support network is.

High levels of anxiety and depression are experienced by some individuals, while others adjust easily, emphasizing the need for patient-centric care.

Psychological Support – An Undervalued Tool

Despite the potential emotional burden, psychological support is not routinely built into Barrett’s oesophagus care pathways; however, some evidence-based therapies can help;

  • Cognitive Behavioural Therapy (CBT) may reduce catastrophic thoughts and improve cancer-related worry.
  • Mindfulness-based approaches can support stress reduction and improve emotional regulation.

Asking for psychological help is appropriate and beneficial for emotional well-being.

What You Can Do to Support Your Well-Being

Although living with Barrett’s oesophagus can feel overwhelming, there are some practical steps that can improve emotional well-being and improve HRQoL:

  • Looking after health by attending checkups.
  • Discussing changes in your condition with clinicians.
  • Taking medication consistently.
  • Identify and avoid reflux triggers (caffeine and alcohol).
  • Create regular routines.
  • Introduce gentle movements and physical activity into daily routines.
  • Prioritise effective sleep strategies

Interacting with support groups, charities and online communities, can help “normalise” emotions and reduce isolation.

Remember, emotions such as frustration, fear, anger and sadness are normal reactions.

Focus on What Can Be Controlled.

Small lifestyle adjustments can create meaningful improvements in both physical and physiological well-being. Stress reduction, diet, trigger avoidance, weight management, and medication adherence contribute to better physical and emotional outcomes. Knowing your health can help manage distorted perceptions of risk and build emotional and physical resilience.

Support Resources within the Island of Ireland

IE/GB: All-Ireland Cancer Research Network (AllCaN)

  • An all-Ireland collaboration researching the well-being of individuals living with Barrett’s oesophagus.
  • Understanding the contributing factors that impact people living with Barrett’s oesophagus.

Website: What is the AllCaN Programme? – All-Ireland Cancer Network

IE – Oesophageal Cancer Fund (OCF) Ireland

OCF provides

  • Patient information resources
  • Emotional support for patients and their families
  • Guidance for people diagnosed with Barrett’s oesophagus

Local GPs and gastroenterology teams can refer patients to counselling services, though individuals often need to request this support. Organizations such as Cancer Support NI and Action Cancer can provide valuable information and emotional assistance. Website: https://ocf.ie.patient-supports.

Living with Barrett’s Oesophagus

The Barrett’s oesophagus journey can be a lonely, emotionally heavy experience, especially when others do not understand the condition. However, research is evolving; charity-funded research programmes such as AllCaN Oesophageal are investing in improving psychological and emotional well-being.

Mental health is just as important as physical health, asking for support can improve an individual’s coping ability and enhance their quality of life.

(Images courtesy of Microsoft 365)

Malaysian-blog

What is it like to be diagnosed with Oesophageal Cancer at a Younger Age?

What is it like to be diagnosed with Oesophageal Cancer at a Younger Age?


Oesophageal Cancer in Younger Adults

Globally, approximately 9% of oesophageal cancers are diagnosed in individuals under the age of 50 years. Although relatively rare, a study from the United States of America and the Netherlands suggest that oesophageal cancer is becoming more common in younger adults under the age of 50. These studies also suggest that younger adults are  often diagnosed at a more advanced stage of disease compared to older adults.

Oesophageal cancer in younger adults has also become more widely discussed in the news.  In November 2025, Zack Van Aarde shared the story of his stage 4  oesophageal cancer diagnosis at the age of 42 on BBC, sharing that “it came as a massive shock”. In March 2026, Dale Atkinson also shared about his life-changing stage 4 oesophageal cancer diagnosis at the age of 35, as reported on Belfast Live.  

Being diagnosed with oesophageal cancer at any age is a shock, not only for patients but also for their families and friends. An oesophageal cancer diagnosis also presents unique challenges for younger adults. It’s important for us to get a better understanding of these issues so we can help to address them. I hope to investigate some of these gaps through my PhD research.


The Experience of Receiving an Oesophageal Cancer Diagnosis

Early detection is very important when it comes to oesophageal cancer. Symptoms of oesophageal cancer often include difficulty swallowing, acid indigestion or heartburn, and food coming back up. The National Health Service (NHS) website provides helpful information on oesophageal cancer symptoms and seeking medical advice. Organisations including the Oesophageal Cancer Fund and OG Cancer NI provide information resources as well as  support networks for individuals impacted by oesophageal cancer.

Understanding how people notice and respond to symptoms of oesophageal cancer is important. Alongside this, exploring how and when people seek medical attention, and understanding the experience of being referred/having tests for cancer is crucial, in order to raise awareness and improve healthcare systems. A 2020 study by Humphrys and colleagues investigated how people in England understood and experienced symptoms before being diagnosed with oesophageal or stomach cancer. This study found that many people didn’t know much about the warning signs beforehand. They often thought their symptoms were due to things like getting older, work, or their lifestyle.

Common symptoms reported in this study included acid reflux, heartburn, indigestion, trouble swallowing, feeling very tired, and losing weight. Most people only decided to see a doctor when the symptoms got worse or didn’t go away, and they usually went to their GP first. However, this study didn’t focus specifically on individuals with oesophageal cancer, or the specific experiences of younger adults aged under 50 years.


The Experience of Receiving an Oesophageal Cancer Diagnosis at a Young Age

As there are limited studies reporting on the experience of younger adults receiving an oesophageal cancer diagnosis, results from studies investigating bowel cancer provide helpful insight. A report by Bowel Cancer UK in 2020 shared that of the young adults diagnosed with bowel cancer, 50% didn’t know that they could develop bowel cancer until their diagnosis, and 40% visited their GP at least three times before referral for further tests. Therefore, a study aiming to understand the experiences of younger adults receiving an oesophageal cancer diagnosis would provide insight into the service needs and unique challenges of younger adults.


My PhD

As part of my PhD, we plan to interview adults under the age of 50 years to better understand what it was like for a younger adult to receive an oesophageal cancer diagnosis in the UK and Ireland. This study will provide insight into the perception of symptoms among individuals under the age of 50 years, as well as the challenges faced around an oesophageal cancer diagnosis. We hope to open recruitment soon.  Through conducting interviews, alongside other studies through my PhD, I aim to contribute to the growing body of research that aims to influence outcomes for patients with early-onset oesophageal cancer.

Lorraine lab pic

A day in the life of a PhD student researching Barrett’s Oesophagus

A day in the life of a PhD student researching Barrett’s Oesophagus.

Hi, I’m Lorraine, a third-year PhD student researching electroporation as a novel therapy for Barrett’s Oesophagus. In this blog, I thought I would share an insight as to what a typical day looks like for a PhD student.

Mornings

Usually, I begin my day with checking my to-do list which like most jobs grows and shrinks depending on the time of year. Often my tasks include preparing presentations, data analysis and following up with orders/deliveries I need for my experiments. With that, I check my emails to follow up with company reps and answer any queries. Normally, I will plan my week on the preceding Friday using Google calendar to schedule my experiments, meetings and set reminders so that I stay on top of deadlines. As I work with patient samples, I also consult the schedule for those which Cian, our Barrett’s Biobank manager shares every Friday and plan my experiments accordingly. On Tuesday and Wednesday mornings I attend our departmental and institutional lab meetings, respectively. These are a great opportunity to learn more about what my colleagues are researching as well as the techniques they are using which often stimulates ideas for my own research. Afterwards, we usually go for coffee to discuss, and this is a lovely way to network and connect with the other researchers.

If I have experiments to do, I like to do them in the mornings or as early in the day as possible. The techniques I most commonly do are cell culture, ELISA, flow cytometry and immunohistochemistry. We are particularly interested in how electroporation affects the Barrett’s Oesophagus microenvironment and its effect on immune system activation. I use both cell line models and tissue samples to study this with each model serving as validation for the other.

Ms Lorraine Smith examining Barrett's Oesophagus tissue under high magnification.

Afternoons

On some days my experiments will also require a lot of the afternoon. However, typically they comprise of analysing data from my experiments. Here, I frequently ask the other PhD students in my office for their opinions on the presentation of the data and other avenues of analysis to pursue. I am very fortunate to be conducting my PhD in a large department where collaborations are common and there is a vast range of expertise. My supervisor is also fundamental in these decisions. I meet with her regularly where we discuss results, ideas and troubleshoot any issues I may be having. Another key task in the afternoons is updating my lab notebook. This a fundamental part of being a scientist. Often the changes made when optimising an experiment are marginal, but it is key for both myself and others after me to understand how the methodology and results came to pass if anything is being repeated. On Fridays, I receive an email alert for new publications in my field. Some weeks this can be 3-4 papers while other weeks there are 20+ papers. I like to end my end by days by checking these for relevance and making notes of any key points which I hope will be useful when writing my thesis and doing my viva examination. Lastly, I check my emails in case there are any that require my attention and update my to-do list for the following day.

The saying “the best-laid plans of mice and men often go awry” is apt for life in research. No two days are the same, some bring exciting results after starting a new experiment while others (most) are filled with trial and error, but which are important steps in the process to new results. Often, when waiting for patient samples, we don’t receive any due to patients not consenting or more frequently if there is an issue with the procedure. On other days, there may be patients added to the schedule, and we might have to rearrange our day to process additional samples. That unpredictability is what keeps this job exciting. We are incredibly lucky to have access to fresh patient samples, and for me this is a particularly meaningful part of my work. I am motivated in knowing that my work will further our understanding of both Barrett’s Oesophagus and electroporation so that this may help to improve patient outcomes. This makes every day I spend in the lab worthwhile.

{"data":{"pictureId":"4D814A7E-B3C9-404C-8ED0-8EE236A01950","activityName":"","imageEffectId":"","filterId":"","playId":"","stickerId":"","os":"ios","appversion":"3.8.0","product":"retouch","infoStickerId":""},"tiktok_developers_3p_anchor_params":"{"filter_id":[],"template_id":"","client_key":"awgvo7gzpeas2ho6"}","source_type":"hypic"}

Understanding Acid Reflux and Barrett’s Oesophagus: The Role of Medications

Understanding Acid Reflux and Barrett’s Oesophagus: The Role of Medications

Around 10-20% of adults in Western countries experience symptoms of gastro-oesophageal reflux disease (GORD) on a weekly basis, with heartburn and acid reflux being the most common symptoms. A smaller proportion, approximately 10-15% of people with long-term GORD symptoms, develop Barrett’s oesophagus during their lifetime. In this blog, I will discuss GORD, its effects on the oesophagus, its potential link to Barrett’s oesophagus, and what current evidence suggests about the role of medications

What is GORD?

Gastro-oesophageal reflux disease, commonly shortened to GORD, occurs when stomach acid flows back into the oesophagus (food pipe), the muscular tube that connects the mouth to the stomach. Under normal conditions, a ring of muscle at the bottom of the oesophagus, known as the lower oesophageal sphincter, acts as a barrier that prevents stomach contents from moving upward. In people with GORD, this barrier may not function effectively, allowing acid to repeatedly enter the oesophagus. Common symptoms of GORD include heartburn, acid regurgitation and noncardiac chest pain.

How acid reflux can affect the oesophagus

The oesophagus functions primarily to transport food and liquids to the stomach, but its lining is not well adapted to repeated exposure to stomach acid. When reflux occurs frequently, the acidic environment can irritate the lining of the oesophagus. This irritation may lead to inflammation and damage to the tissue.

Over time, the body may respond to this repeated irritation by altering the type of cells that line the lower part of the oesophagus. These cellular changes provide insight into how chronic reflux may affect the oesophageal lining.

GORD and Barrett’s Oesophagus

One possible outcome of chronic acid reflux is Barrett’s oesophagus. In this condition, the cells lining the lower oesophagus undergo abnormal changes. This change is thought to occur as an adaptive response to repeated exposure to stomach acid.

Barrett’s oesophagus itself does not usually cause noticeable symptoms beyond those associated with reflux. However, it is considered a precursor that carries an increased risk of developing oesophageal adenocarcinoma. It is important to note that most people with Barrett’s oesophagus do not develop cancer, and studying its progression from GORD helps explain how the oesophageal lining changes.

Medications and Acid Reflux

Medications that reduce stomach acid are commonly used to manage symptoms of GORD: two main types are widely used in clinical practice:

Proton pump inhibitors (PPIs) are commonly prescribed medications that reduce the amount of acid produced in the stomach. They work by blocking the proton pumps in the acid-producing cells of the stomach lining. These pumps are responsible for the final step in acid production. By inhibiting them, PPIs lower the amount of acid in the stomach, which helps relieve symptoms of acid reflux.

Another group of medications, known as H2 receptor blockers, also reduce acid production but through a different biological mechanism. These drugs block histamine type 2 receptors that stimulate acid secretion in the stomach. This decreases acid secretion and thereby helps to control symptoms of acid reflux.

Many studies in the field of pharmacoepidemiology examine how medications are used in large populations and how their use relates to health outcomes. By analysing healthcare databases and prescription records, these studies can identify patterns of medication use and explore whether long-term use is associated with differences in the risk or progression of conditions such as Barrett’s oesophagus or oesophageal cancer, contributing to a better understanding of how these medications may influence oesophageal health.

Infographic: Created using https://BioRender.com

My research is currently funded by Breakthrough Cancer Research and The Department for the Economy.


Malaysian-blog

What Do We Know About Oesophageal Adenocarcinoma in Younger People?

About Me

My name is Abigail, and I am a first-year PhD student at Queen’s University Belfast. I completed my undergraduate degree in Biomedical Science in 2022 at Queen’s University Belfast, and later pursued my Masters of Public Health in Global Health at Queen’s University Belfast as well. During my undergraduate degree, I completed a summer studentship at the Northern Ireland Cancer Registry, where I developed an interest in how cancer occurs in different groups of people (also known as Cancer Epidemiology). I would like to continue in the field of Cancer Epidemiology, and I am therefore very excited to be working on a project investigating oesophageal cancer in younger people in Ireland, based in the Centre for Public Health at Queen’s University Belfast.

How Common is Oesophageal Adenocarcinoma?

Oesophageal adenocarcinoma is one of two common subtypes of oesophageal cancer that commonly occurs in the lower part of the oesophagus. It is the most common subtype in countries such as Australia, Canada, and other countries in Western and Northern Europe and North America. It is also more common in men. Having gastroesophageal reflux and being overweight/obese can increase an individual’s risk of developing oesophageal adenocarcinoma. 

In Northern Ireland, between the years 2018 and 2022, 1,109 individuals were diagnosed with oesophageal cancer, 9.4% of whom were under 54 years of age. In the Republic of Ireland, between 2017 and 2021, there were 2,522 oesophageal cancer diagnoses, 10.5% of whom were under 54 years of age.  

What is Barrett’s Oesophagus?

Barrett’s oesophagus is a condition where the cells that line the oesophagus have changed to resemble cells that line the intestine. While there is a chance that these cells can progress to oesophageal adenocarcinoma, not all individuals with Barrett’s oesophagus will develop oesophageal adenocarcinoma. In Northern Ireland, for example, only 0.3% of people with Barrett’s oesophagus progress to develop oesophageal adenocarcinoma per year.

What Do We Know About Oesophageal Adenocarcinoma in Younger People?

Oesophageal adenocarcinoma, especially in younger individuals under 50 has become an increasingly important area of research, as a study has indicated a more than three-fold increase in diagnoses among individuals under 50 years of age between 1975 and 2015 in the United States of America. Despite relatively limited research focusing on younger patients, findings suggest that younger patients may present at a more advanced stage of disease compared to older patients. It remains unclear if there are differences in survival outcomes among younger patients compared to older individuals with oesophageal adenocarcinoma, indicating the need for further investigation.

While these studies have been instrumental in forming our understanding of oesophageal adenocarcinoma in younger people, there still are gaps in the research in this age group. More studies into risk factors and trends in oesophageal adenocarcinoma among younger people would be essential pieces of the larger puzzle of the landscape of oesophageal adenocarcinoma in younger people.

What’s Next?

To answer the question “what do we know about younger people with oesophageal adenocarcinoma?”, turns out there is still much to find out! There is a need for more studies investigating the oesophageal adenocarcinoma subtype in younger patients specifically. Considering evidence of a rise in oesophageal adenocarcinoma in younger people, there is an urgent need for more research in this age group.

The island of Ireland is home to incredible cancer databases in the form of cancer registries. These registries have been recognised to have high quality population level data. Through my PhD project, I aim to bring together data from these databases to:

  • to investigate the incidence and survival of younger people with oesophageal adenocarcinoma across the island of Ireland
  • identify trends in the incidence of oesophageal adenocarcinoma among younger people on the island of Ireland
  • investigate some of the reasons why we are seeing an increase in oesophageal adenocarcinoma in younger people, such as obesity and Barrett’s oesophagus
  • contribute to the growing body of evidence globally

Alongside analysing the data on oesophageal adenocarcinoma in younger people, it is also important to hear from patients themselves about their experiences. Therefore, I plan to speak to younger patients with an oesophageal adenocarcinoma diagnosis about their lived experience, which will give us a clearer picture of the specific needs of younger patients. This would be the first study on the island of Ireland investigating the lived experience of younger patients.

thumbnail_image (2)

Digital Pathology and AI: Enhancing Barrett’s Oesophagus Diagnosis

When you think of a “pathologist,” you might picture a person in a lab coat, looking at slides containing patient tissue under a microscope. In fact, if you search for “pathologist” online, most pictures will show that. But the job has changed a lot recently. Now, instead of just using a microscope, pathologists can take digital pictures of the slides and like photos on your phone, can view them on a computer. This helps them work faster as they are able to get second opinions quicker instead of sending a slide by post.

As the records are all digitised (in Northern Ireland since 2022) this means sample tracking has become much more robust, which makes it easier to figure out what’s wrong. This is important because pathologists help other doctors figure out about 70% of all medical diagnoses, and in Northern Ireland, there are 40 million pathological diagnostic tests every year.

Diagnosis of Barrett’s oesophagus is one of these tests (Figure 1). Barrett’s oesophagus can be found by looking at tiny pieces of tissue under a microscope, taken from your food pipe (or gullet) during a procedure called an endoscopy. Once a pathologist identifies Barrett’s oesophagus, they need to also look for the potential presence of dysplasia. But what does “dysplasia” mean? This is when cells in the body start growing in the wrong way. If enough cells become abnormal, it may lead to cancer. Pathologists sort Barrett’s into four types:

  1. Non-Dysplastic (normal cells).
  2. Indefinite for Dysplasia (not sure if the cells are abnormal).
  3. Low-Grade Dysplasia (cells starting to look different).
  4. High-Grade Dysplasia (cells look very different).

Figure 1. Diagnosis of Barrett’s Oesophagus following endoscopy (Created in  https://BioRender.com).
A. Clinician performs endoscopy examination.
B. Biopsies are taken from the food pipe and processed onto a glass slide.
C.1. Traditionally a microscope would be used to view patient’s samples.
C.2. Modern pathology involves scanning and viewing slides on a computer.
D. Pathologist reviews tissue slides.
E. Pathologist grades samples.
F. Secondary tests and opinions. Digital pathology allows multicenter options for review.
G. Follow up appointments and monitoring.

The good news is, most people with Barrett’s oesophagus have the non-dysplastic type, which means they’re very unlikely to get cancer of the oesophagus. Previous research from the Northern Ireland Barrett’s oesophagus register has estimated that three people in every one hundred will progress to cancer over a ten year timeframe. For the few people with the other types of Barrett’s, it’s really important to figure out what type of dysplasia is present. To determine this, the tissue samples are sent to another pathologist to check again and because the tissue images are now digital, pathologists from different places can view these, which makes it faster to find problems. They will also use a method called Immunohistochemistry (IHC). IHC uses antibodies to detect proteins in tissues samples. One of the proteins they test for is p53 which is often expressed in dysplastic Barrett’s oesophagus and is an early marker for cancer (BSG Guidelines).

While identifying Barrett’s is straightforward, distinguishing between the four types of Barrett’s oesophagus still proves challenging for pathologists. In 2018 a large population-based study from the Northern Ireland Barrett’s register showed that around 13% of patients with high grade dysplasia or oesophageal adenocarcinoma were likely to be
misdiagnosed with Barrett’s oesophagus
(non-dysplastic or low-grade) initially as they then developed high-grade dysplasia or oesophageal adenocarcinoma within the 3-12 months post-prior to their diagnosis. This is where Artificial Intelligence (AI) could help. Some studies have shown that AI can not only help doctors diagnose Barrett’s oesophagus but also help figure out how serious it is through identifying dysplasia and the types of Barrett’s.

Other ways AI can help is through surveillance, by identifying for example a morphological feature within the tissue which can stratify a patient’s risk of progression to cancer.

I got the chance to talk to Dr. Damian McManus, a pathologist with more than 30 years of experience. He told me how tools, like AI, are helping doctors find and treat diseases more quickly and accurately.

Dr Damian McManus, Senior Lecturer and Consultant Pathologist

Richard: How long have you been a pathologist?

Damian: I started training in 1990, passed MRCPath in 1996 and was appointed as Consultant in 1998 (27 years consultant experience).

Richard: How have you found your job has changed over time? ie When was digital pathology introduced and has it sped-up diagnosis?

Damian: The three big changes in my professional career have been increased sub specialisation, increasing use of IHC and molecular tests for diagnosis and as predictive markers and the introduction of digital pathology for primary reporting. As I write this, I am at a conference so I can’t check when digital was implemented: it was the summer of 2021 or 2022.

Richard: What is the current standard procedure for a Barrett’s diagnosis and Grading in your work?

Damian: We currently diagnose Barrett’s oesophagus when columnar mucosa is found on biopsy in the oesophagus. This may show intestinal metaplasia or there may be columnar mucosa which is more like gastric mucosa or a mixture of both. Correlation with the endoscopic findings is mandatory and very important. Most Barrett’s oesophagus biopsies are negative for dysplasia. A minority show dysplasia; this may be classified as low grade or high grade. In line with BSG guidance all dysplasia samples have an independent second read by a second pathologist and immunohistochemistry for p53 and MIB1 is used frequently.

Richard: Day to day what is the biggest challenge when it comes to oesophageal biopsy examination and Barrett’s diagnosis?

Damian: Distinction between dysplasia and reactive atypica secondary to ulceration and active inflammation is still probably the most problematic; the category of indefinite for dysplasia is the categorisation used if the pathologist is not sure, although it is important to use this category sparingly.

Richard: Do you currently use AI in your job?

Damian: Not currently in histological diagnosis. Large language models like ChatGPT can be very useful in undergraduate and postgraduate teaching.

Richard: How do you feel about the introduction of AI to your field of work?

Damian: I think that it is inevitable that it will be introduced and that it might ultimately change the role of the pathologist.

Richard: Where do you feel AI could assist you most with Barrett’s Diagnostics?

Damian: In many NHS laboratories there are large backlogs of routine cases; models such as Paige’s Virchow model could help triage these cases and detect unsuspected cancers

Richard: How important is human intervention in the world of AI for diagnostic purposes?

Damian: Currently it is still very important, and the pathologist still has to make the final decision…. Although who knows how long that will last.

From the conversation with Dr McManus, it is evident that AI could prove helpful in a Barrett’s diagnostic setting alongside a pathologist. A major limiting factor in AI in the diagnostic setting is the vast range of data it requires to perform efficiently. A multicenter approach and agreed guidelines for Barrett’s oesophagus are required – both of which are currently not in place. For my project I aim to use Northern Ireland Barrett’s Register data and AI to identify a novel biomarker which will help stratify Barrett’s oesophagus patients on their risk of developing oesophageal cancer which will prioritise surveillance strategies.

Authors: Mr. Richard Murray and Dr Damian McManus.

Victoria

Unlocking New Possibilities through The Northern and Southern Barrett’s Oesophagus Registeries

All about me

I’m Victoria Child and I’m a Research Fellow at Centre for Public Health Queen’s University, Belfast. I completed my undergraduate and PhD studies in Nutrition at the Coleraine campus of Ulster University on the scenic North Coast of Northern Ireland. Following my studies, my love of research and desire to ultimately improve the care experience for individuals living with chronic disease led me to pursue a career in Public Health research. Alongside my work, I enjoy spending time doing things that balance out the demands of my professional life including sewing, cake decorating, spending time with friends and family and volunteering at a variety of local community-based youth and women’s organisations.

My journey in cancer and premalignant epidemiology and surveillance started in 2014, firstly working in the Northern Ireland Cancer Registry and most recently in my role as project manager for the Northern Ireland Barrett’s oesophagus register. My current role is jointly funded by Breakthrough Cancer Research and Oesophageal Cancer Fund as part of the All-Ireland Oesophageal Cancer (AllCaN oesophageal) network. This network seeks to to bring together two unique large-scale Barrett’s oesophagus registry data across the island of Ireland, for the first time.


The Foundation of the Northern Ireland Barrett’s oesophagus Register

The Northern Ireland Barrett’s oesophagus register was established in the early 1990s by Professor Liam Murray with the help of pump priming funding from the Ulster Cancer Foundation, now known as Cancer Focus NI. Further updates and funding for the registry were supported by the UK Medical Research Council and the HSC R&D Office Northern Ireland.  Its current stewardship lies with Professor Helen Coleman, thanks to funding via a Fellowship from Cancer Research UK, working with a clinical steering group comprising Professor Brian Johnston (Gastroenterology), Dr Damian McManus (Pathology) and Dr Richard Turkington (Oncology). It is one of the largest population-based registers worldwide with data on more than 28,000 individuals diagnosed with Barrett’s oesophagus in Northern Ireland since 1993.

With over £2.6 million invested across three decades, the register is not just a data repository, it’s a key resource for advancing epidemiological, clinical research and forms a sampling frame for groundbreaking biomarker studies all aimed at better understanding and managing Barrett’s oesophagus.


Key Findings from the Northern Ireland Barrett’s oesophagus Register

 Several important discoveries have emerged from the Northern Ireland registry data collected, which have been instrumental in shaping our understanding of Barrett’s oesophagus:

  1. Rising Incidence: Between 1993 and 2005, the number of new cases of Barrett’s oesophagus in Northern Ireland increased by 150%, underscoring the need for more effective detection and surveillance strategies.
  2. Low Cancer Progression: Despite concerns, the progression to oesophageal adenocarcinoma in patients with Barrett’s oesophagus is surprisingly low, ranging from 0.2% to 0.4%. This offers reassurance but also highlights the need to identify the small group of patients at higher risk.
  3. Identifying Risk Factors: The register has highlighted key risk factors for progression to oesophageal adenocarcinoma, including tobacco smoking, ulceration within Barrett’s segments, and certain biomarkers. These insights allow doctors to focus their attention on high-risk patients for more intensive monitoring.
  4. Survival Benefits of Surveillance: Perhaps the most encouraging finding is that regular surveillance significantly improved survival rates for those patients with Barrett’s oesophagus who went on to get oesophageal adenocarcinoma. This reinforces the importance of early detection of Barrett’s oesophagus and ongoing check-ups for those diagnosed with Barrett’s oesophagus.

The accompanying biomarker research underway, working in conjunction with Dr Richard Turkington and collaborators, aims to further deepen our understanding by determining how long someone has had Barrett’s and pinpointing biological factors linked to cancer progression—ultimately helping doctors identify those Barrett’s patients in need of closer monitoring.

National Barrett’s register, Ireland

The National Barrett’s Oesophagus Registry, launched in Ireland in 2009 through a large programme grant from Oesophageal Cancer Fund (OCF).  The hospital-based register is directed by Professor John Reynolds Upper GI Consultant, St. James’s Hospital in collaboration with Professor Jacintha O’Sullivan professor in Translational Oncology at the Trinity Translational Medicine Institute (TTMI), Trinity College Dublin and it plays a critical role in the fight against oesophageal cancer through early detection. With over €1.5 million in funding, the registry links six major hospitals in Ireland, including St. James’s, St. Vincent’s, Beaumont, and others. To date, nearly 9,000 patients have been included.

The registry helps healthcare professionals identify at-risk patients early, using endoscopies and biopsies to detect cellular changes like dysplasia or early-stage cancer. Early diagnosis means oesophageal cancer can be addressed at its most treatable stage. For patients whose condition progresses, Radio Frequency Ablation (RFA) therapy is offered, a highly effective procedure that removes diseased tissue and promotes the growth of healthy tissue.

Oesophageal Cancer Fund donations also fund a National Barrett’s Biobank, which collects tissue and blood samples from consenting patients. These samples fuel crucial research, helping scientists understand the biological factors that drive cancer progression and improve patient care.

The National registry’s work continues to make a huge impact on early detection and treatment of oesophageal cancer.

The Future: Unlocking New Possibilities through All-Ireland Collaboration

The AllCaN oesophageal network which has received €1million funding from Breakthrough Cancer Research has enabled a major new research initiative on the island of Ireland to bring together data these two Barrett’s oesophagus registers: the Northern Ireland Barrett’s register and the National Barrett’s registry to build a unique resource which aims to:

  1. Combine diagnostic data from more than 34,000 patients to explore trends in the number of people diagnosed with Barrett’s oesophagus and dysplasia across both Northern Ireland and the Republic of Ireland.
  2. Analyse treatment data from around 1,000 patients with dysplasia or early-stage cancer, focusing on endoscopic treatments. This research will compare how treatments are administered across the two health service systems, looking at treatment timing, intervals between diagnosis and treatment, and patient outcomes.

Working together with our collaborators and Patient and Public Involvement panel members, I am excited to be driving innovations and new insights into Barrett’s oesophagus and oesophageal cancer prevention through analysis of these fantastic Irish data resources. More information on the National Barrett’s Register (Ireland) can be found here.




